

Many couples in Malaysia first raise fertility with the same gynaecologist they see for check-ups or period problems. That is a sensible place to start. General guidance in many countries suggests seeking assessment after about a year of regular unprotected sex without a pregnancy, or after six months if the woman is 35 or older. Irregular cycles, known endometriosis or previous pelvic surgery are reasons to raise it sooner.
Some gynaecologists focus on fertility and reproductive medicine, and clinics often publish profiles that show training and areas of interest. Reading the clinic’s doctor profiles before a referral helps you understand who handles what, especially if your care may move between general gynaecology and assisted reproduction.
A fertility assessment looks at both people. For the woman, that commonly includes blood tests for hormones such as AMH, which gives a rough sense of ovarian reserve, plus an ultrasound of the uterus and ovaries. A check of the fallopian tubes, such as an HSG, may follow. For the man, a semen analysis looks at count, movement and shape. It is a simple test, and skipping it can waste months.
The American College of Obstetricians and Gynecologists patient FAQ on treating infertility outlines how these results guide the choice between monitoring, medication, insemination and IVF. No single test predicts the outcome on its own. The combination tells the story.
Intrauterine insemination places washed, concentrated sperm directly into the uterus around ovulation. It may be done in a natural cycle or alongside medication that encourages one or more eggs to mature. The procedure itself is brief and is often compared to a smear test. It generally needs at least one open fallopian tube and reasonable sperm parameters to make sense.
The UK fertility regulator’s HFEA guide to IUI is frank about who it suits and how results vary. A local page on how insemination cycles are usually explained shows how a Malaysian clinic describes the timing and steps.
Clinics usually monitor the cycle with ultrasound, and sometimes blood tests, to time the insemination. When medication is used, the aim is a small number of mature follicles, because too many raises the chance of a multiple pregnancy. How many IUI cycles are reasonable before rethinking the plan depends on age and the underlying cause, and that is worth discussing early rather than after many months.
A reproductive medicine team talks through the practical differences between IUI and IVF.
In vitro fertilisation moves fertilisation into the laboratory. The ovaries are stimulated to produce several eggs, which are collected in a short procedure under sedation. Eggs and sperm are then combined, sometimes by injecting a single sperm into each egg, and the resulting embryos are grown for a few days before one is transferred. Remaining good-quality embryos may be frozen for later use.
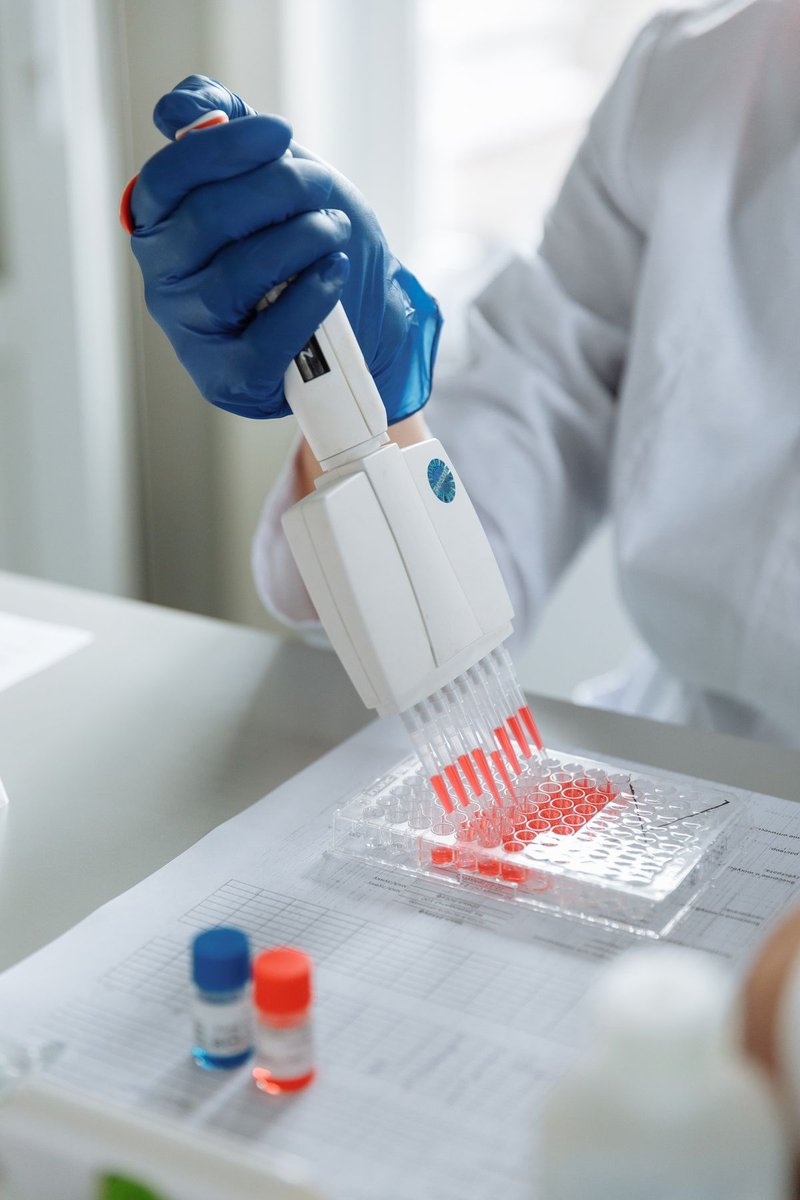
IVF is often discussed for blocked tubes, significant male factor issues, older age or after several unsuccessful IUI cycles. The NHS overview of IVF covers the steps and the common risks, including ovarian hyperstimulation and multiple pregnancy. A Malaysian centre’s overview of IVF adds local context on how cycles are organised.
Good counselling is specific. It explains why each test is ordered and which result would change the plan. It gives success figures by age band rather than one headline number, and it says plainly when a treatment is unlikely to help. It also covers the emotional and financial weight of repeated cycles, and when it might be reasonable to pause, switch approach or stop.
A consultation that leaves you with only optimism and no numbers has not finished its job. The most useful clinicians tend to be comfortable saying “we do not know yet”, and then explaining exactly what would help them find out.